

A landmark 2026 PROTECT study, involving 174 older adults, has demonstrated the significant potential of self-administered fingerprick blood tests for remote Alzheimer’s risk triage. The research found that levels of phosphorylated tau at amino acid 217 (p-tau217) correlated meaningfully with episodic memory, a cognitive domain frequently impacted early in Alzheimer’s disease, while glial fibrillary acidic protein (GFAP) showed an association with working memory. These findings support the utility of such remote testing as a preliminary screening tool to identify individuals at higher risk, rather than a definitive diagnostic instrument for dementia.
The Urgent Need for Accessible Alzheimer’s Screening
The global burden of Alzheimer’s disease and related dementias is immense and growing. With an aging population worldwide, the prevalence of these neurodegenerative conditions is projected to escalate dramatically, posing significant challenges to healthcare systems and economies. Early and accurate diagnosis is critical for several reasons: it allows patients and families to plan for the future, provides access to available treatments that can slow cognitive decline, and facilitates participation in clinical trials for new therapies. However, current diagnostic pathways often involve specialized clinics, invasive procedures, and considerable travel, creating significant barriers to access, particularly for individuals in rural areas, those with limited mobility, or those facing socioeconomic disadvantages.
Traditional diagnostic methods for Alzheimer’s disease typically involve a combination of clinical interviews, cognitive assessments, neurological examinations, and often advanced neuroimaging (such as MRI, PET scans for amyloid or tau pathology) or cerebrospinal fluid (CSF) analysis. While highly accurate, these methods can be costly, time-consuming, and inaccessible to many. The development of blood-based biomarkers has revolutionized the field, offering less invasive and more scalable alternatives. Plasma p-tau217, in particular, has emerged as a highly specific marker for Alzheimer’s-type tau and amyloid pathology, showing strong diagnostic accuracy in venous blood. GFAP, a marker of astrocyte activation, provides insights into neuroinflammation and broader brain injury, including vascular pathology. The PROTECT study sought to push these advancements further by investigating whether these powerful biomarkers could be reliably measured from a simple, at-home fingerprick.
Study Design and Participants: A Low-Friction Approach to Remote Sampling
The PROTECT research program, a long-running initiative focused on understanding and preventing dementia in the UK, provided the ideal cohort for this innovative study. Researchers recruited 226 individuals from the program, ultimately analyzing data from 174 participants who successfully completed the at-home blood-test kits. The final study group comprised a diverse population with a mean age of 66.03 years, 54% female, including 146 individuals with normal cognition and 28 diagnosed with dementia. This inclusion of both cognitively healthy and impaired individuals was crucial for assessing the biomarkers’ ability to differentiate between states of cognitive health.
The study’s workflow was deliberately designed to be "low-friction," emphasizing ease of use and remote accessibility. Participants received mailed kits containing all necessary materials for self-collection of capillary blood via a fingerprick. Detailed instructions ensured proper collection, and samples were then returned to a central laboratory for analysis. This streamlined process aimed to mimic a real-world remote screening scenario, evaluating not just the biological efficacy of the markers but also the practical feasibility and user experience. The inherent advantage of capillary sampling lies in its reach; unlike venous blood draws that necessitate clinic visits or phlebotomy services, fingerprick samples can be integrated with computerized cognitive testing, mailed kits, and remote trial-screening workflows, vastly expanding the potential pool of individuals who can be screened.
Key Findings: Biomarker Performance and Cognitive Associations
The study yielded compelling results regarding the performance of both p-tau217 and GFAP in capillary blood. Capillary p-tau217 demonstrated its strongest cognitive association with episodic memory (r = 0.299, p < 0.001). Episodic memory, which involves the recall of specific events and personal experiences, is a cognitive domain most visibly and typically affected in the early stages of Alzheimer’s disease. Beyond episodic memory, p-tau217 also correlated with other crucial cognitive functions, including attention and executive function, as well as both functional measures used in the study, indicating a broad impact on daily living.
GFAP, while also showing significant associations, presented a broader and less Alzheimer-specific pattern. It correlated with working memory, executive function, and instrumental activities of daily living (IADLs), which encompass complex daily tasks like managing finances or medications. However, GFAP did not correlate with the IQCODE functional informant measure, which assesses changes in daily function reported by a knowledgeable informant. Intriguingly, the researchers also noted a relationship between elevated GFAP levels and the presence of heart disease. This observation suggests that GFAP’s elevation might reflect a wider range of underlying pathologies, including neuroinflammation and vascular injury, in addition to Alzheimer’s-related glial responses. This distinction aligns with previous research where plasma p-tau217 has shown high specificity in discriminating Alzheimer’s disease from other neurodegenerative disorders, while GFAP’s utility, though valuable, is broader due to astrocyte activation occurring in various injury pathways.
Thresholds for Risk Identification: Identifying Higher-Risk Subgroups
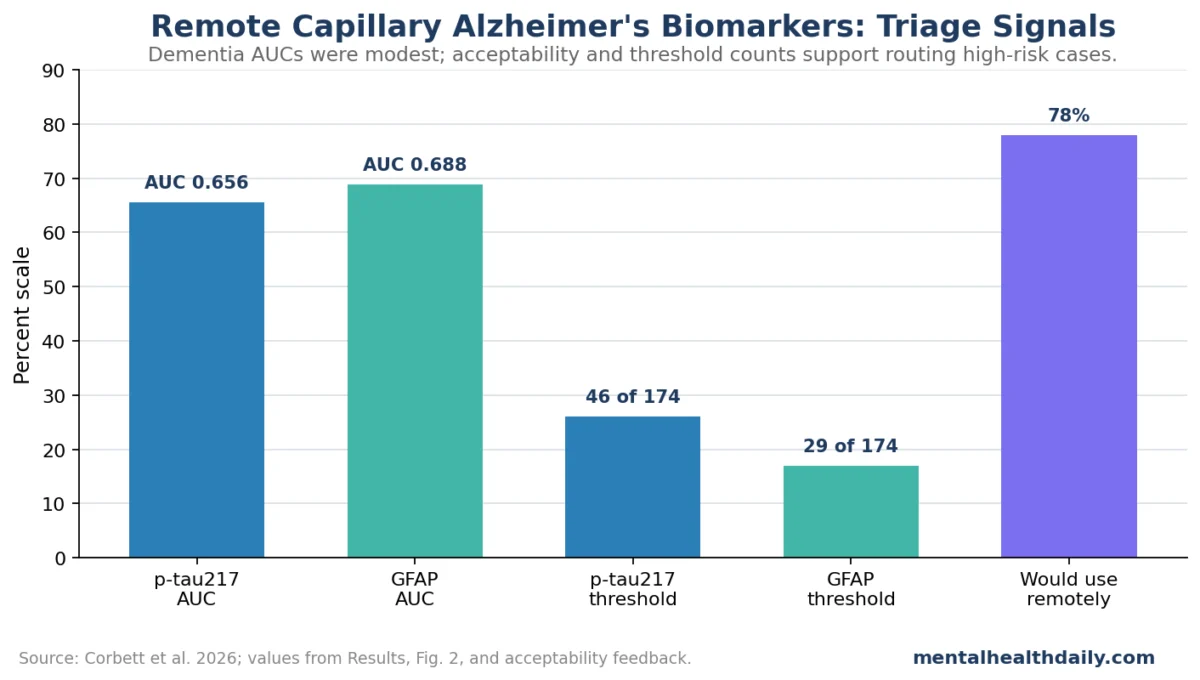
To assess the practical utility of these biomarkers for triage, Corbett et al. established prespecified 85% specificity thresholds: 0.016 pg/ml for capillary p-tau217 and 12.45 pg/ml for capillary GFAP. Applying these thresholds, the study identified 46 participants (26% of the cohort) with elevated p-tau217 and 29 participants (17%) with elevated GFAP.
Crucially, individuals exceeding these thresholds exhibited demonstrably poorer performance on several cognitive and functional measures. For those with elevated p-tau217, memory differences showed a Cohen’s d of 0.548 (p = 0.020), IADL differences were d = 0.542 (p = 0.017), and IQCODE differences were d = 0.657 (p = 0.001). Cohen’s d values indicate the effect size, with values around 0.5 suggesting a medium-sized practical difference. For participants with elevated GFAP, the IADL difference was even larger at d = 0.754 (p = 0.004), and executive function showed a difference of d = 0.541 (p = 0.016). These findings underscore that elevated levels of these capillary biomarkers are indeed associated with tangible cognitive and functional impairments.
Furthermore, the study confirmed that these capillary-derived thresholds were recognizable in venous plasma. Plasma p-tau217 effectively discriminated the capillary p-tau217 threshold group with an Area Under the Curve (AUC) of 0.785, while plasma GFAP discriminated its capillary counterpart with an impressive AUC of 0.895. These high AUC values are critical, demonstrating that the remote capillary measurements align well with established venous blood chemistry, thus validating their biological relevance and preventing them from being mere "artifacts" of the self-collection method.

Triage, Not Diagnosis: The Crucial Distinction
A central tenet emphasized by the PROTECT study is the distinction between "triage" and "diagnosis." While the capillary biomarkers showed significant correlations with cognitive function and could identify higher-risk subgroups, their diagnostic accuracy (as measured by AUC values for separating dementia vs. non-dementia status) was 0.656 for p-tau217 and 0.688 for GFAP. These values are better than chance but are not considered "diagnostic-grade." An AUC of 1.0 represents perfect discrimination, while 0.5 is no better than random guessing. Values in the 0.6-0.7 range suggest some predictive power but also considerable overlap between cases, meaning many individuals with and without dementia would not be correctly classified by the blood test alone.
Therefore, the study strongly advocates for a "combined triage profile." This involves integrating elevated p-tau217 (above the 85% specificity threshold) with memory performance low enough to meet age-associated cognitive-decline criteria. Such a combination could effectively identify individuals who warrant a more rapid and formal dementia evaluation than what a symptom questionnaire alone might suggest.
The clinical role of these remote markers is thus envisioned as a powerful tool to sort risk, reduce screen failures in clinical trials, and optimize the allocation of scarce specialist appointments towards those with the highest biological signal of underlying pathology. Critically, these tests should not be used to provide a definitive Alzheimer’s diagnosis to a person at home without further clinical context and confirmatory testing. A normal result also cannot completely rule out non-Alzheimer causes of cognitive decline, very early pathology below the detection threshold, or future disease progression.
Implications for Healthcare Access and Clinical Trials
The practical advantages of remote capillary sampling are profound, particularly concerning healthcare access. Many individuals experiencing early cognitive impairment never enter specialist diagnostic pathways due to various barriers: geographical distance to memory clinics, lack of transportation, limited clinic capacity, or the perceived burden of participating in screening for clinical trials. A mailed capillary kit can significantly lower these barriers, potentially reaching underserved populations and enabling broader participation in research. This "access effect" is a powerful argument for the adoption of such technologies.
Clinical trials, especially those focused on Alzheimer’s prevention and early intervention, stand to benefit immediately. These trials often require screening large numbers of participants to identify a smaller cohort with a specific biomarker profile (e.g., amyloid positivity) suitable for the study. Fingerprick p-tau217 could substantially reduce the number of expensive screen failures by pre-identifying individuals more likely to possess confirmatory amyloid or tau evidence, thereby streamlining recruitment processes and reducing overall research costs.
Navigating the Ethical Landscape: Responsibilities and Boundary Conditions
While the potential benefits are clear, the study also highlights crucial responsibilities and ethical considerations. Lowering the barrier to screening inherently increases the responsibility to avoid overdiagnosis, unnecessary anxiety, or inappropriate medical interventions. A remote positive result must not leave a patient with a label but without a clear route forward. Instead, it should trigger a defined sequence of follow-up actions: comprehensive cognitive testing, medical review, and, when appropriate, confirmatory assessment through imaging or cerebrospinal fluid analysis.
A workable pathway for managing these results would involve distinct roles:
- Remote Triage: Identifying individuals at higher risk through combined biomarker and cognitive screening.
- Primary Care Physician: Interpreting the triage results within the broader clinical context, considering other factors like medications, lifestyle, and comorbidities.
- Specialist Evaluation: Conducting definitive diagnosis and treatment planning for those referred from primary care.
The distinction between p-tau217 and GFAP is also vital here. P-tau217 is more directly indicative of Alzheimer’s biology, while GFAP may flag broader neuroinflammatory or vascular risks. A triage algorithm that treats both markers as interchangeable "Alzheimer positive" signals would flatten this useful distinction. For instance, a person with elevated GFAP and a history of vascular disease might primarily require aggressive vascular risk management, whereas someone with elevated p-tau217 and declining memory would necessitate an Alzheimer’s workup. Managing false positives effectively is paramount to prevent misdirection of care.
The Road Ahead: Longitudinal Validation and Comprehensive Care
For remote screening to move from promising triage research into routine primary care pathways, longitudinal validation is the missing link. The most valuable future outcome is not merely whether a capillary marker correlates with memory at a single point in time, but whether it reliably predicts future conversion to dementia, faster cognitive decline, or eligibility for specific treatment trials over several years. This long-term evidence is essential to demonstrate that remote screening improves patient outcomes, reduces harms, and is cost-effective.
Furthermore, implementation needs a robust plan for managing "low-signal" results. A low capillary biomarker result should never dismiss a caregiver’s report of worsening memory, medication errors, falls, hallucinations, or financial mistakes. Instead, it should narrow the immediate probability of Alzheimer’s-specific biomarker pathology while keeping the broader differential diagnosis open. In primary care, conditions such as depression, sleep apnea, anticholinergic medications, alcohol exposure, hearing loss, and cerebrovascular disease can all mimic early dementia symptoms. A comprehensive clinical approach, integrating biomarker data with a thorough medical history and clinical judgment, remains indispensable.
The PROTECT study represents a significant stride towards more accessible and equitable Alzheimer’s risk assessment. By validating the utility of self-administered fingerprick blood tests for remote triage, it opens new avenues for early detection, clinical trial recruitment, and ultimately, a more proactive approach to managing neurocognitive disorders. However, the findings underscore that these powerful new tools must be integrated thoughtfully into a comprehensive healthcare framework, ensuring that technological advancement translates into genuine improvements in patient care, guided by caution and clinical wisdom.

