

The global fitness and rehabilitation industries are currently navigating a significant paradigm shift regarding the language used during client assessments and the subsequent implementation of corrective exercise protocols. For decades, a dominant trend among personal trainers and physical therapists has been the identification of "dysfunction" as the primary objective of an initial consultation. This approach, often characterized by the diagnostic labeling of minor postural deviations and movement variances, is increasingly being scrutinized by industry leaders who argue that pathologizing normal human movement variability may be detrimental to both client progress and the economic health of the fitness sector.
The Linguistic Landscape of Movement Assessment
In the contemporary fitness environment, professionals are often inundated with complex terminology designed to categorize human movement. Terms such as dorsiflexion, diastasis recti, disc herniation, and density sets are staples of the professional lexicon. However, experts are now pointing toward the word "dysfunction" as the most problematic term in the industry. The critique suggests that the overuse of this word creates a "nocebo effect," wherein a client begins to perceive themselves as fundamentally "broken" or "failed" before they have even begun a training program.
The traditional assessment model frequently involves a "litany of errors" approach. During an initial session, a coach may highlight an internally rotated shoulder, anterior pelvic tilt, thoracic kyphosis, or a lack of rotation on a specific side. While these observations may be anatomically accurate, the manner in which they are communicated often positions the client as a "walking ball of fail." This diagnostic-heavy approach is increasingly viewed as a barrier to entry for many individuals seeking to improve their health, as it replaces the motivation of movement with the anxiety of "fixing" perceived defects.
Scapular Winging and the Misapplication of Clinical Diagnoses
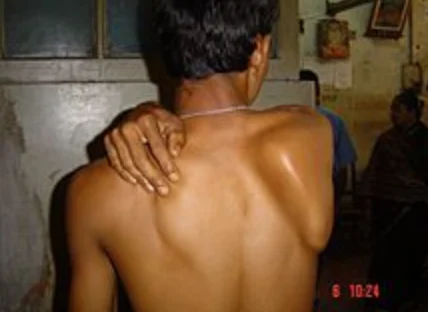
A primary example of the tension between clinical pathology and movement variability is found in the assessment of the scapula. Scapular winging—a condition where the medial border of the shoulder blade protrudes from the rib cage—is frequently cited by fitness professionals as a major "dysfunction" requiring immediate corrective intervention.
However, a critical distinction must be made between true clinical scapular winging and general movement variance. True scapular winging is a medical diagnosis often resulting from damage to the long thoracic nerve, which prevents the serratus anterior muscle from pinning the scapula against the thoracic wall. In such cases, traditional fitness exercises like prone trap raises or forearm wall slides are often insufficient, as the issue is neurological rather than purely mechanical. This condition requires specialized manual therapy and neurological intervention.
In contrast, many individuals exhibit what appears to be "winging" due to lack of muscular development, poor awareness, or simply natural anatomical variation. Industry data suggests that a significant portion of the population exhibits some degree of scapular prominence without associated pain or loss of function. The emerging consensus among strength and conditioning specialists is that these individuals are not "dysfunctional." Instead of "corrective exercise purgatory"—a cycle of low-intensity isolation movements that rarely yield performance gains—many coaches are finding that the application of "load" and traditional strength training is the most effective remedy. By challenging the body with resistance, the nervous system often self-organizes into more efficient positions, effectively "fixing" the movement through performance rather than isolation.
A Chronology of the Corrective Exercise Era
The rise of the "dysfunction-first" model can be traced back to the late 1990s and early 2000s, following the mainstream adoption of various movement screening systems.
- 1990s – The Physiotherapy Influence: Strength coaching began to incorporate more concepts from physical therapy, leading to a heightened awareness of "injury prevention" and "pre-habilitation."
- Early 2000s – The Screening Boom: The introduction of standardized movement screens allowed trainers to "score" movement. While intended to identify risk, it often led to a culture of over-diagnosis.
- 2010s – Corrective Exercise Purgatory: The industry saw a peak in "activation" drills. Clients would often spend 30 to 40 minutes of an hour-long session performing low-intensity movements to "turn on" specific muscles.
- 2020 to Present – The Rise of Movement Optimism: A growing movement, supported by educators like Tony Gentilcore and others involved in programs such as the "Even More Complete Shoulder & Hip Blueprint," advocates for a "training-centric" approach. This model prioritizes what a client can do over what they cannot.
Supporting Data: The Prevalence of Asymptomatic Deviations
The argument against the "dysfunction" label is supported by a wealth of radiological and clinical data. Studies have consistently shown that anatomical "abnormalities" are common in asymptomatic populations.
- Lumbar Spine: Research published in the American Journal of Neuroradiology found that 30% of 20-year-olds and 84% of 80-year-olds have disc bulges despite having no back pain.
- Shoulder Health: Studies on overhead athletes have shown that a high percentage of "healthy" pitchers have labral tears that do not impede their performance or cause pain.
- Knee Anatomy: Meniscal tears are frequently found in the knees of middle-aged adults who report zero pain or functional limitations.
These data points suggest that "dysfunction" on paper or in a visual assessment does not necessarily correlate with "dysfunction" in life or sport. When fitness professionals overemphasize these findings, they risk creating psychological barriers that prevent clients from engaging in the very activity—heavy resistance training—that would likely improve their structural integrity.
The Economic and Psychological Impact on the Fitness Industry
The shift away from "dysfunction" is not merely a matter of semantics; it is a business imperative. Fitness professionals are increasingly reporting that the "broken" narrative leads to higher client attrition rates. When a client’s first interaction with a professional is a list of their physical failures, the "barrier to entry" becomes psychological.
Behavioral psychologists note that "self-efficacy"—the belief in one’s ability to succeed in specific situations—is one of the strongest predictors of long-term exercise adherence. By highlighting "dysfunction," trainers actively undermine a client’s self-efficacy. Conversely, an assessment that focuses on "movement audits" to find "entry points" for training fosters a sense of competence.
The financial implications are clear: clients who feel capable and strong are more likely to continue their programs, whereas those who feel they are a "dumpster fire" of orthopedic issues are more likely to become discouraged and quit.
Official Responses and Professional Standards
Leading organizations in the fitness space have begun to update their curricula to reflect this more nuanced view. The National Academy of Sports Medicine (NASM) and the American Council on Exercise (ACE) have historically provided frameworks for corrective exercise, but recent continuing education modules have placed a greater emphasis on "regression and progression" rather than "fixing."
Prominent strength coaches have voiced their support for this evolution. The prevailing sentiment is that the role of the fitness professional is to "audit" movement to determine the best starting point for a client’s goals, injury history, and current ability, rather than to act as a pseudo-medical diagnostic tool. The goal is to set people up for success by finding movements they can perform well under load, rather than keeping them in a state of perpetual "correction."
Broader Implications and the Future of Coaching
The move toward "movement optimism" suggests a future where the line between rehabilitation and performance is increasingly blurred. By focusing on "training through" rather than "fixing first," coaches are seeing faster results in both strength gains and pain reduction.
The implications for the broader health sector are significant. As the fitness industry moves away from pathologizing movement, it positions itself as a more accessible partner in public health. The "D-word" (dysfunction) is being replaced by words like "adaptation," "variability," and "potential."
In conclusion, the evolution of the fitness industry highlights a critical maturation. Professionals are moving away from the need to prove their expertise by finding fault in their clients. Instead, the modern standard of excellence is being defined by the ability to take a client—regardless of their "scapular winging" or "anterior pelvic tilt"—and find a path to high-performance training that respects their current anatomy while building future resilience. The focus has shifted from what is "wrong" to what is possible, marking a new era of movement science centered on empowerment rather than pathology.

