

A groundbreaking 2026 PROTECT study, involving 174 older adults, has revealed that self-administered fingerprick tests measuring plasma p-tau217 and glial fibrillary acidic protein (GFAP) correlate with key cognitive functions, offering a significant step towards remote Alzheimer’s risk triage. The research, published following the study conducted through the UK PROTECT program, found a statistically significant correlation between self-administered fingerprick p-tau217 levels and episodic memory (r = 0.299, p < 0.001), while GFAP levels correlated with working memory (r = 0.183, p = 0.034). These findings strongly support the utility of remote capillary blood sampling as a tool for identifying individuals at higher risk for Alzheimer’s disease, thereby streamlining referral pathways for formal evaluation, rather than serving as a definitive, stand-alone dementia diagnosis.
The Evolving Landscape of Alzheimer’s Diagnosis
Alzheimer’s disease (AD) represents the most common form of dementia, affecting millions worldwide. Its insidious onset and progressive neurodegeneration pose immense challenges to individuals, families, and healthcare systems. Historically, a definitive diagnosis of AD could only be confirmed post-mortem through neuropathological examination. In recent decades, advancements in neuroimaging (PET scans for amyloid and tau pathology) and cerebrospinal fluid (CSF) analysis have revolutionized ante-mortem diagnosis, allowing for earlier and more accurate identification of AD pathology. However, these methods are often invasive, expensive, and require specialized clinical settings, limiting their widespread accessibility, particularly in primary care or underserved regions.
The quest for simpler, more accessible, and less invasive diagnostic tools has thus become a paramount focus in Alzheimer’s research. Blood-based biomarkers have emerged as a particularly promising avenue, offering the potential for scalable and cost-effective screening. The development of highly sensitive assays capable of detecting minute quantities of AD-related proteins in plasma has transformed the field, bringing the vision of routine blood tests for Alzheimer’s a significant step closer to reality.
Understanding the Biomarkers: p-tau217 and GFAP
Central to the PROTECT study’s findings are two key blood biomarkers: p-tau217 and GFAP.
-
p-tau217 (phosphorylated tau at amino acid 217): Tau is a protein abundant in neurons, where it plays a crucial role in stabilizing microtubules, essential components of the cell’s cytoskeleton. In Alzheimer’s disease, tau becomes abnormally phosphorylated, leading to its aggregation into neurofibrillary tangles, one of the hallmark pathologies of AD. Elevated levels of specific phosphorylated tau isoforms in the blood, particularly p-tau217, are now recognized as highly specific indicators of Alzheimer’s-type tau and amyloid biology in the brain. Plasma p-tau217 has demonstrated remarkable accuracy in distinguishing AD from other neurodegenerative disorders and even from healthy aging, often reflecting early pathological changes years before clinical symptoms manifest. Its specificity to AD pathology makes it an invaluable tool for targeted screening.
-
GFAP (glial fibrillary acidic protein): GFAP is an intermediate filament protein primarily found in astrocytes, which are star-shaped glial cells that play critical roles in supporting neurons, maintaining the blood-brain barrier, and regulating the brain’s immune response. When the brain experiences injury, inflammation, or neurodegeneration, astrocytes become activated, a process known as astrogliosis. Elevated levels of GFAP in the blood serve as a marker of this astrocyte activation. While GFAP can reflect Alzheimer-related glial responses, it is a broader indicator and can also rise due to other conditions such as neuroinflammation, vascular injury, or even traumatic brain injury. This makes GFAP a useful, albeit less specific, marker for general brain health and injury, providing complementary information to highly specific markers like p-tau217.
Both p-tau217 and GFAP have already demonstrated superior performance in venous blood compared to many traditional, older dementia-screening tools, which often rely on subjective cognitive assessments or less specific measures. The PROTECT study aimed to push the boundaries further by exploring a narrower, yet highly practical, operational question: could older adults successfully collect capillary blood at home, and would the biomarker values derived from these self-collected samples still align reliably with cognitive function, overall functional status, venous blood measurements, and positive user feedback?
The PROTECT Study: Pioneering Remote Capillary Sampling
The PROTECT study, a longitudinal online cohort study based in the UK, is at the forefront of investigating brain health and cognitive aging. Its infrastructure provides an ideal platform for evaluating novel remote diagnostic and screening methods. For this particular investigation, the study initially recruited 226 individuals from the broader PROTECT research program. Of these, 174 participants successfully completed the at-home blood-test kits and were included in the final analysis. The cohort was diverse, comprising 146 individuals with normal cognition and 28 individuals already diagnosed with dementia. The mean age of the participants was 66.03 years, with a slight majority (54%) being female.
The workflow for self-administered capillary blood collection was meticulously designed to be "low-friction," emphasizing ease of use and minimal technical requirements for participants. This approach is crucial for any screening tool intended for widespread home use, particularly among an older demographic who may have varying levels of technological proficiency or physical dexterity. The practical advantage of such a low-friction workflow is its unparalleled reach. Unlike traditional venous blood testing, which necessitates a visit to a clinic or phlebotomy service, capillary sampling can be seamlessly integrated with existing remote healthcare infrastructures. This includes computerized cognitive testing, mailed kits containing all necessary components, and streamlined remote trial-screening workflows, effectively removing geographical and logistical barriers to participation.
Key Findings: Unpacking the Biomarker-Cognition Link
The study’s results provided compelling evidence for the utility of self-administered capillary blood tests:
-
p-tau217: A Specific Alzheimer’s Indicator: Capillary p-tau217 demonstrated its strongest and most specific cognitive association with episodic memory. Episodic memory, which involves the recall of specific events, times, and places, is the memory system most visibly and profoundly affected early in the typical progression of Alzheimer’s disease. This finding strongly reinforces p-tau217’s role as a highly specific marker for AD pathology. Beyond episodic memory, p-tau217 also correlated with other crucial cognitive domains, including attention and executive function, as well as both functional measures assessed in the study (which likely included instrumental activities of daily living, IADLs, and informant-based questionnaires).
-
GFAP: A Broader Marker of Brain Health: In contrast, GFAP exhibited a broader, but less Alzheimer-specific, pattern of correlations. It was significantly associated with working memory, executive function, and instrumental activities of daily living (IADLs), which encompass complex daily tasks like managing finances or taking medication. However, GFAP did not show a significant correlation with the IQCODE (Informant Questionnaire on Cognitive Decline in the Elderly) functional informant measure, suggesting its signal might be less directly tied to the everyday functional decline observed by caregivers. Importantly, the researchers also reported a relationship between elevated GFAP levels and a history of heart disease, further substantiating the interpretation that GFAP can reflect broader vascular and inflammatory processes in addition to specific Alzheimer-related astrogliosis.
This observed split in specificity aligns well with adjacent biomarker research. Studies by Palmqvist et al. (reference 2 in the original article) have robustly shown that plasma p-tau217 can effectively discriminate Alzheimer’s disease from other neurodegenerative disorders, underscoring its diagnostic precision. Similarly, Ashton et al. (reference 3) have reported strong diagnostic accuracy for plasma p-tau217 immunoassays against confirmed Alzheimer’s pathology. While GFAP undoubtedly holds clinical utility as a marker for general brain injury and inflammation, its less direct connection to specific Alzheimer’s pathology means that astrocyte activation, which it reflects, can arise from various injury pathways, making it a less precise "Alzheimer label" compared to p-tau217.
Thresholds and Risk Stratification: Identifying Higher-Risk Subgroups
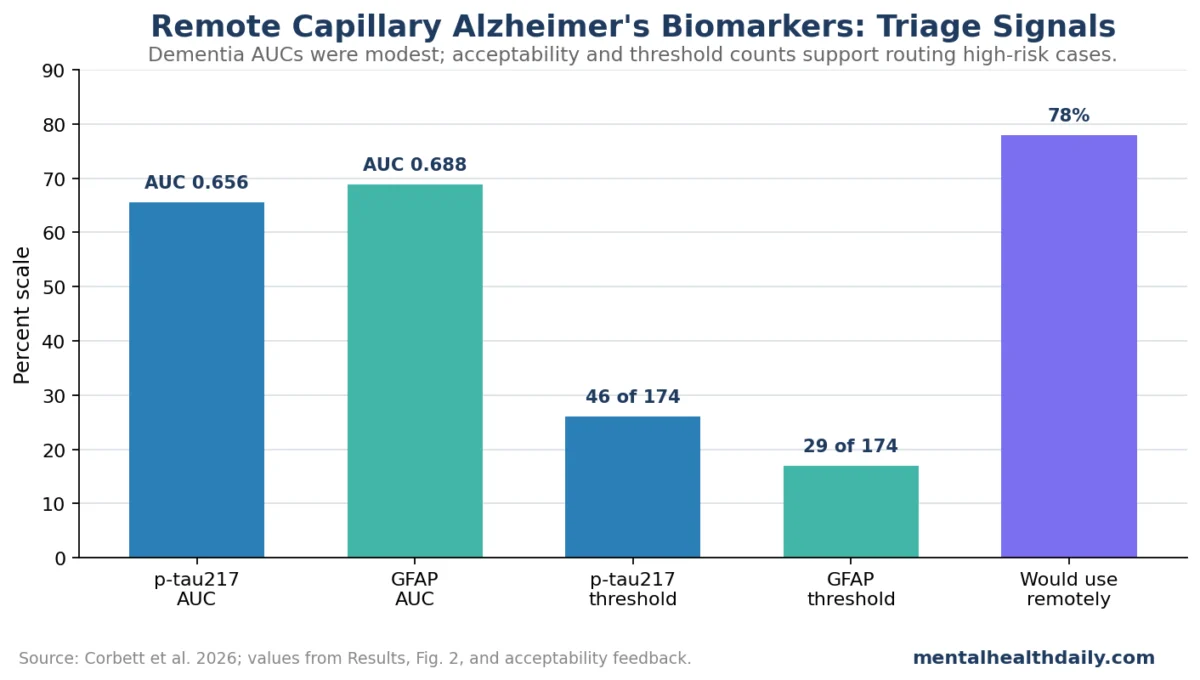
To further explore the clinical applicability, Corbett et al. employed prespecified 85% specificity thresholds for both capillary biomarkers: 0.016 pg/ml for p-tau217 and 12.45 pg/ml for GFAP. These thresholds are critical as they allow for the identification of individuals whose biomarker levels fall into a range indicative of higher risk. Applying these thresholds, the study identified 46 participants (26% of the cohort) with elevated p-tau217 and 29 participants (17%) with elevated GFAP.

Crucially, individuals whose biomarker levels exceeded these thresholds consistently performed worse on several cognitive or functional measures. For those with elevated p-tau217, significant differences were observed in memory performance (Cohen’s d = 0.548, p = 0.020), IADL scores (d = 0.542, p = 0.017), and IQCODE scores (d = 0.657, p = 0.001). These Cohen’s d values, representing effect sizes, indicate meaningful differences between the high-risk and low-risk groups. For GFAP, the IADL difference was even larger (d = 0.754, p = 0.004), and executive function also showed a significant difference (d = 0.541, p = 0.016).
A critical validation of the remote sampling method came from the comparison with venous plasma. The same thresholds established for capillary blood were recognizable in venous plasma, with plasma p-tau217 discriminating the capillary p-tau217 threshold group with an Area Under the Curve (AUC) of 0.785, and plasma GFAP discriminating the capillary GFAP threshold group with an impressive AUC of 0.895. This strong concordance is vital, as it confirms that the remote capillary kit is not producing a separate, uninterpretable artifact, but rather mapping onto established blood chemistry, thereby establishing its clinical utility.
The Clinical Idea: Remote Capillary Sampling as a Triage Tool
The most potent clinical idea emanating from the PROTECT paper is the concept of a combined triage profile. This would involve identifying individuals whose p-tau217 levels are above the 85% specificity threshold and whose memory performance is low enough to meet age-associated cognitive decline criteria. Such a combination could effectively identify people who should be fast-tracked for formal dementia evaluation, moving them through the diagnostic pipeline more efficiently than relying solely on symptom questionnaires, which can be subjective and less sensitive to early pathological changes.
It is imperative to underscore the distinction between risk sorting (triage) and definitive diagnosis. The study’s AUC values for separating dementia vs. non-dementia status were 0.656 for capillary p-tau217 and 0.688 for GFAP. While these values indicate that the tests perform better than chance, they are not at a diagnostic grade (which typically requires AUCs closer to 0.90 or higher for high confidence). A normal result from these remote tests also cannot definitively rule out non-Alzheimer causes of cognitive decline, early pathology that falls below the threshold, or future conversion to dementia. The clinical role of remote p-tau217 and GFAP is therefore to sort risk, reduce screen failures in clinical trials by prescreening suitable candidates, and direct scarce specialist appointments towards individuals with a higher biological signal of potential AD. They should unequivocally not be used to tell a person at home that they have Alzheimer’s disease.
The distinction is not merely semantic. An AUC of 0.656 means that there is still significant overlap between dementia and non-dementia cases based on capillary p-tau217 levels. GFAP is even less disease-specific, as astrocyte activation can increase due to vascular injury, inflammation, general neurodegeneration, and mixed pathologies, requiring careful clinical interpretation. The most useful application of this test, therefore, is as a referral aid. The blood result should be combined with a comprehensive clinical picture, including detailed memory performance assessments, reports on daily function from the patient and informants, a thorough medication review, depression screening, sensory assessments (e.g., hearing and vision loss, which can mimic cognitive decline), and an assessment of vascular-risk history. Only after integrating all these factors should a decision be made regarding the need for confirmatory imaging (such as amyloid or tau PET scans), cerebrospinal fluid testing, or specialist neurological evaluation.
Broader Impact and Implications: Transforming Access and Clinical Trials
The advent of remote capillary blood testing holds profound implications for healthcare access and the efficiency of clinical research.
-
Enhancing Access and Equity: The "access effect" is a critical advantage. Many individuals with early cognitive impairment never enter specialist pathways due to significant barriers such as long travel distances, lack of public transport, limited clinic capacity, or the burden associated with trial screening. A mailed capillary kit can dramatically lower these barriers, reaching people in rural areas, those with mobility issues, or individuals in underserved communities. This democratization of access is a powerful argument for its implementation. However, lowering the barrier to initial testing simultaneously increases the responsibility on the healthcare system to avoid overdiagnosis and ensure appropriate follow-up. The equity argument is strongest when the test expands access to confirmatory follow-up and care, rather than replacing it with an incomplete assessment.
-
Streamlining Clinical Trials: Clinical trials, particularly those for Alzheimer’s prevention and early intervention, face significant challenges in recruitment. These trials often require screening large numbers of participants to identify a smaller, specific group with the correct biomarker profile (e.g., amyloid positivity). This prescreening process is notoriously expensive and time-consuming, often leading to high screen failure rates. Fingerprick p-tau217 could revolutionize this process by providing an efficient and cost-effective initial screen, identifying individuals who are more likely to have confirmatory amyloid or tau evidence. This would significantly reduce the financial burden and logistical complexity of trial recruitment, accelerating the pace of research.
-
The Need for a Confirmatory Pathway: For remote testing to be clinically useful, a well-defined confirmatory pathway is indispensable. A remote positive result must not leave the patient with a distressing label and no clear route forward. Instead, it should trigger a defined sequence of further cognitive testing, comprehensive medical review, and, when appropriate, confirmatory assessment by specialists. This pathway would ideally separate three distinct jobs: (1) remote capillary sampling and initial cognitive screening, (2) detailed cognitive testing and medical review by primary care or a specialized nurse, and (3) specialist evaluation, potentially including advanced imaging or CSF analysis, for definitive diagnosis and treatment planning.
-
Distinguishing Biomarker Signals: The study highlights a crucial "boundary condition": p-tau217 is most closely linked to Alzheimer’s biology, whereas GFAP may identify broader neuroinflammatory or vascular risk. A triage algorithm that treats both markers as interchangeable "Alzheimer positive" signals would flatten the most useful distinction provided by the paper. Managing false positives is also paramount. A person with elevated GFAP and vascular disease may benefit more from aggressive vascular-risk management than from an Alzheimer’s label, which could lead to unnecessary anxiety and misdirected interventions. Conversely, a person with elevated p-tau217 and declining memory warrants a focused Alzheimer’s workup. Keeping these routes separate and tailored to the specific biomarker profile is what makes the biomarker pair clinically useful.
Challenges and Future Directions: The Missing Link
While the PROTECT study marks a significant advance, several challenges must be addressed before remote screening can move from triage research into routine primary-care pathways.
-
Longitudinal Validation: The most critical missing link is longitudinal follow-up. The current study demonstrates a correlation between capillary markers and cognitive function at a single point in time. However, for a screening program to be truly useful, it needs evidence that remote biomarker-plus-cognition profiles can predict future diagnosis, faster cognitive decline, or eligibility for treatment trials over several years. This long-term predictive power is the cornerstone for establishing the clinical utility of any screening tool.
-
Routine Population Screening vs. Targeted Triage: While the evidence is strong enough to justify more validation of remote triage, especially in trial recruitment and specialist-referral enrichment, routine population screening presents a harder claim. Broad screening programs require robust evidence that testing demonstrably improves patient outcomes, reduces harms (e.g., anxiety, unnecessary procedures), and is cost-effective at a population level. A single cross-sectional correlation study, no matter how promising, cannot fully answer these complex implementation questions.
-
Comprehensive Clinical Context: Even with a positive remote result, the interpretation by a clinician remains essential. A mailed kit can reach people far from memory clinics, but the result still needs to be integrated by a healthcare professional who can inquire about medications (e.g., anticholinergic drugs), alcohol use, sleep patterns, depression, sensory impairment (hearing loss, vision problems), vascular risk factors, education level, and day-to-day functional challenges. All these factors can significantly influence cognitive performance and contribute to a differential diagnosis.
-
Managing Low-Signal Results: Equally important is a plan for managing low-signal results. A low capillary biomarker result should never dismiss a caregiver’s report of worsening memory, medication errors, falls, hallucinations, or financial mistakes. Instead, it should narrow the immediate probability of Alzheimer’s biomarker pathology while keeping the broader differential diagnosis open. This is especially crucial in primary care, where conditions like depression, sleep apnea, anticholinergic drug side effects, chronic alcohol exposure, hearing loss, and cerebrovascular disease can all present with symptoms that mimic early dementia to families.
Conclusion
The 2026 PROTECT study offers compelling evidence that self-administered fingerprick blood tests for p-tau217 and GFAP are viable tools for remote Alzheimer’s risk triage. By correlating with key cognitive domains and aligning with established venous blood markers, these tests pave the way for more accessible and equitable early risk assessment, particularly for clinical trial recruitment and directing specialist referrals. However, it is critical to reiterate that these are triage tools, not diagnostic ones. Their effective implementation requires robust longitudinal validation, clear confirmatory pathways, and integration into a comprehensive clinical assessment that considers the full spectrum of factors influencing cognitive health. The future of Alzheimer’s care is increasingly moving towards earlier detection and intervention, and remote blood-based biomarkers are poised to play a pivotal role in this transformative journey, provided they are deployed responsibly and within a well-structured clinical framework.

