

The fitness and strength and conditioning industries are currently undergoing a significant paradigm shift regarding the language used during client assessments, specifically concerning the term dysfunction. For decades, the standard operating procedure for personal trainers and physical therapists involved a rigorous "audit" of a client’s movement patterns, often resulting in a laundry list of perceived physical failings. This approach, while intended to be thorough, is increasingly being scrutinized for its potential to instill a "nocebo effect" in clients, leading to a perception of being "broken" or "fragile." As industry leaders advocate for a move away from pathological terminology, the focus is shifting toward movement optimism, the use of external load as a corrective tool, and a clearer distinction between anatomical variance and clinical pathology.
The Psychosocial Impact of Negative Labeling in Fitness
The initial assessment is a critical juncture in the trainer-client relationship. Historically, professionals have utilized this time to demonstrate their expertise by identifying every minute deviation from a "textbook" posture. Common findings presented to clients include internal shoulder rotation, anterior pelvic tilt, thoracic kyphosis, and lack of joint-specific rotation. While these observations may be anatomically accurate, the delivery often frames them as "dysfunctions" that require urgent "fixing."
Psychological research into the nocebo effect—where negative expectations lead to negative outcomes—suggests that this language can be detrimental. When a client is told they are a "walking ball of fail," it can lead to kinesiophobia (fear of movement) and decreased self-efficacy. Professional maturation within the coaching community has led to the realization that highlighting every minor imperfection may actually hinder business retention and client progress. Instead of feeling empowered to begin a fitness journey, clients may feel overwhelmed by a "corrective exercise purgatory" that prioritizes low-intensity rehabilitation over the actual training goals they sought to achieve.
Anatomical Variance versus Clinical Pathology: The Case of Scapular Winging
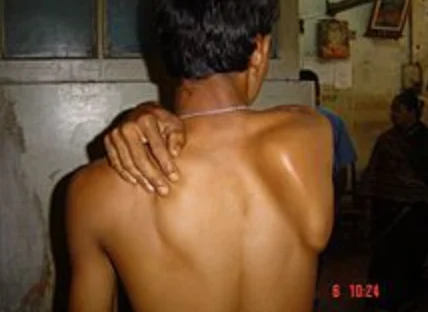
A primary example of the over-pathologization of movement is the assessment of scapular winging. Scapular winging occurs when the medial border of the shoulder blade protrudes from the rib cage rather than lying flat against it. In a clinical setting, true scapular winging is a serious medical diagnosis often resulting from palsy of the long thoracic nerve, which innervates the serratus anterior muscle. This condition represents a genuine neurological dysfunction that requires specialized medical intervention and manual therapy.
However, in the general population, many individuals exhibit what appears to be minor scapular winging. In the majority of these cases, the long thoracic nerve is fully functional. The "winging" is often a result of poor muscular recruitment, lack of general strength, or simply natural anatomical variation. Data suggests that a significant percentage of the asymptomatic population exhibits some form of "postural abnormality" when scrutinized under a lens of perfection. By labeling these individuals as dysfunctional, fitness professionals may be overstepping their scope of practice and misdiagnosing a simple lack of conditioning as a medical crisis.
The Chronology of the Corrective Exercise Era
To understand the current shift, one must look at the timeline of movement assessment trends over the last thirty years.
- The Late 1990s to Early 2000s (The Rise of Functionalism): This era saw the birth of the "functional movement" movement. Tools like the Functional Movement Screen (FMS) became industry standards. The focus shifted from muscle-building to movement quality. While revolutionary, it led to an era where trainers became hyper-focused on "corrective exercises."
- The Mid-2010s (The Peak of Corrective Purgatory): During this period, it was common for a 60-minute personal training session to include 40 minutes of foam rolling, stretching, and low-level activation drills, leaving little time for actual strength training. The word "dysfunction" reached its peak usage during this time.
- 2020 to Present (The Movement Optimism Shift): Led by figures such as Tony Gentilcore, Dr. Quinn Henoch, and the Barbell Medicine group, the industry began to push back. The focus returned to the idea that the human body is resilient and adaptable. The consensus shifted toward the idea that "movement is medicine" and that most minor "dysfunctions" resolve themselves through progressive overload and proper coaching.
Supporting Data on Posture and Pain Correlation
The drive to remove "dysfunction" from the fitness lexicon is supported by an increasing body of evidence suggesting a weak correlation between static posture and pain. A landmark study by Brinjikji et al. (2015) analyzed MRI findings in asymptomatic individuals—people with no back pain. The study found that 37% of 20-year-olds and 96% of 80-year-olds had disk degeneration. Furthermore, 30% of 20-year-olds had disk bulges despite having no symptoms.
These findings have profound implications for the fitness industry. If "abnormal" structural findings are common in pain-free populations, then labeling a client’s anterior pelvic tilt or minor scapular winging as a "dysfunction" is scientifically tenuous. Data indicates that movement quality exists on a spectrum, and what one coach calls a "fault," another may see as an individual’s unique leverage or structural adaptation to their environment.
The Economic and Professional Implications for Fitness Providers
From a business perspective, the "dysfunction-first" model has proven to be a double-edged sword. While it initially establishes the trainer as an authority figure, it can create a barrier to entry for the client. If a client’s goal is weight loss or muscle gain, but they are told they cannot lift weights until their "scapular upward rotation is optimized," they are likely to lose motivation.
Industry analysts suggest that trainers who adopt a "strength-first" approach—incorporating correctives into a lifting program rather than replacing the program with them—see higher retention rates. By using load (weight) to nudge people into better positions, trainers can achieve two goals simultaneously: improving movement quality and providing the physiological stimulus the client is paying for. For instance, a goblet squat can often "fix" a squatting pattern more effectively than dozens of unweighted mobility drills because the anterior load forces the core to engage and the center of mass to shift backward.
Official Responses and Industry Standards
Major certifying bodies, such as the National Academy of Sports Medicine (NASM) and the American Council on Exercise (ACE), have begun to update their curricula to reflect a more nuanced view of assessment. While they still teach movement screens, there is an increased emphasis on the "Positive Coaching Alliance" model, which focuses on what a client can do.
Prominent strength coaches have voiced their support for this transition. The general consensus among top-tier professionals is that the term "dysfunction" should be reserved for clinical settings where a true loss of function is present (e.g., a torn ligament, a nerve palsy, or a fractured bone). For the average gym-goer, the preferred terminology is shifting toward "movement compensations" or "technical deviations," which carry less psychological weight and imply a simpler path to improvement.
Broader Impact: Bridging the Gap Between Rehab and Performance
The de-emphasis of the word "dysfunction" is also helping to bridge the gap between physical therapy (rehab) and strength coaching (performance). When both sectors stop viewing the human body as a machine that is constantly "breaking down" and start viewing it as an organism that adapts to stress, the transition from injury recovery to athletic training becomes seamless.
The modern approach suggests that "corrective exercise" is simply "good coaching." If a client’s knees cave in during a squat, it isn’t necessarily a "dysfunction" of the gluteus medius; it may simply be a technical error that requires a verbal cue or a slight adjustment in foot position. By removing the pathological labels, trainers allow clients to focus on progress rather than pathology.
Conclusion: The Path Forward
The fitness industry’s move away from the "D-word" represents a maturation of the profession. By acknowledging that most people are not "broken" but simply "untrained," fitness professionals can foster an environment of growth and confidence. The focus is returning to the fundamentals: training with intent, applying progressive load, and respecting the vast range of normal human movement. As the industry continues to evolve, the goal remains the same—setting people up for the most success possible given their goals, history, and abilities—but the language used to get there is becoming significantly more empowering. The "dysfunction" era is giving way to an era of resilience, where the emphasis is no longer on what is wrong with the body, but on what the body is capable of achieving.

