

A landmark 2026 PROTECT study, involving 174 older adults, has demonstrated the viability of self-administered fingerprick blood tests for p-tau217 and GFAP as valuable tools for remote Alzheimer’s risk triage, rather than immediate dementia diagnosis. The findings, published recently, indicate that capillary p-tau217 levels correlated significantly with episodic memory (r = 0.299, p < 0.001), while GFAP levels showed an association with working memory (r = 0.183, p = 0.034). This research marks a significant step towards making preliminary Alzheimer’s risk assessment more accessible, potentially transforming how individuals are identified for further clinical evaluation, especially in diverse and underserved populations.
The study emerges at a critical juncture in Alzheimer’s research, as the global healthcare community grapples with the escalating prevalence of dementia and the persistent challenges in early, accurate diagnosis. Traditional diagnostic pathways for Alzheimer’s disease often involve extensive neurological examinations, cognitive assessments, expensive and sometimes invasive imaging techniques like PET scans, or cerebrospinal fluid (CSF) analysis, which requires a lumbar puncture. These methods can be costly, time-consuming, and geographically restrictive, creating significant barriers to early detection and intervention, particularly for individuals in rural areas or those with limited access to specialized medical centers. The advent of blood-based biomarkers has offered a less invasive and more scalable alternative, with markers like p-tau217 and GFAP showing increasing promise in reflecting underlying brain pathology. However, even these blood tests typically require a visit to a phlebotomy clinic for venous blood draw, a logistical hurdle that the PROTECT study sought to address by exploring the feasibility of home-based capillary blood collection.
Understanding the Biomarkers: p-tau217 and GFAP
Central to the study’s findings are two critical biomarkers: p-tau217 and GFAP. P-tau217, or phosphorylated tau at amino acid 217, is a highly specific blood marker known to rise when Alzheimer’s-type tau and amyloid biology are present in the brain. Its specificity makes it a powerful indicator of Alzheimer’s pathology, differentiating it from other neurodegenerative conditions. Glial Fibrillary Acidic Protein (GFAP), on the other hand, is a marker of astrocyte activation. Astrocytes are star-shaped glial cells in the brain and spinal cord that support neurons and maintain the blood-brain barrier. When activated, GFAP levels can reflect various pathological processes, including neuroinflammation, vascular injury, or a general Alzheimer-related glial response. While GFAP is clinically useful, its broader indicative nature means it is less specific to Alzheimer’s disease than p-tau217, as astrocyte activation can stem from multiple injury pathways. Both markers have already demonstrated stronger performance in venous blood samples compared to many older dementia-screening tools, setting the stage for investigating their utility in a more accessible format.
The PROTECT Study: Pioneering Remote Capillary Sampling
The PROTECT (Prospective Online Testing of Cognition and other health markers) study, a UK-based research program, aimed to address a very specific operational question: could older adults successfully collect capillary blood samples at home, and would these samples yield biomarker values that accurately correlated with cognitive function, overall health, venous blood results, and positive user feedback? This ambitious goal reflected a growing need for remote, user-friendly diagnostic and screening tools in an increasingly digitized healthcare landscape.
The study initially recruited 226 individuals from the PROTECT research program, ultimately analyzing data from 174 participants who successfully completed the self-administered blood-test kits. The final cohort had a mean age of 66.03 years, with 54% female representation, and included a mix of 146 individuals with normal cognition and 28 diagnosed with dementia. This diverse group allowed researchers to evaluate the biomarkers’ performance across a spectrum of cognitive statuses. The workflow was intentionally designed to be "low-friction," emphasizing ease of use and minimal imposition on participants. This involved mailing comprehensive kits directly to participants’ homes, providing clear instructions for self-collection of capillary blood via a simple fingerprick, and facilitating the return of samples via postal services. This streamlined approach minimizes the need for clinic visits, phlebotomist appointments, and specialized equipment, thereby significantly expanding the reach of potential screening.
The practical advantage of this remote capillary sampling approach is undeniable: reach. Unlike venous blood testing, which necessitates a clinical setting or a phlebotomy pathway, capillary sampling can be seamlessly integrated with computerized cognitive testing, mailed kits, and remote trial-screening workflows. This paves the way for a more inclusive and efficient system for identifying individuals at risk, especially those who face geographical or logistical barriers to traditional healthcare access.
Key Findings: Differentiating Marker Specificity and Impact
The study meticulously analyzed the correlations between the self-collected capillary biomarkers and various cognitive and functional measures. Capillary p-tau217 demonstrated its strongest cognitive association with episodic memory, which is the memory system most visibly affected early in typical Alzheimer’s disease. Episodic memory refers to the recollection of specific events, situations, and experiences. Beyond episodic memory, p-tau217 also correlated with attention, executive function, and both functional measures assessed in the study, underscoring its broad relevance to cognitive health impacted by Alzheimer’s pathology.
GFAP, while also showing significant correlations, presented a broader but less Alzheimer-specific pattern. It correlated with working memory (the ability to hold and manipulate information in mind for short periods), executive function (higher-level cognitive skills like planning and problem-solving), and instrumental activities of daily living (IADLs), which encompass complex tasks like managing finances, cooking, and shopping. However, GFAP did not correlate with the IQCODE (Informant Questionnaire on Cognitive Decline in the Elderly) functional informant measure, which assesses changes in daily functioning as reported by a close acquaintance. Researchers also reported a notable relationship between elevated GFAP levels and a history of heart disease, suggesting that vascular and inflammatory interpretations of GFAP elevation are highly plausible.
This differential pattern of association aligns with adjacent biomarker research. Previous studies, such as those by Palmqvist et al., have shown that plasma p-tau217 can effectively discriminate Alzheimer’s disease from other neurodegenerative disorders. Similarly, Ashton et al. reported strong diagnostic accuracy for a plasma p-tau217 immunoassay against confirmed Alzheimer’s pathology. While GFAP can be clinically useful for indicating general neuroinflammation or injury, it serves as a less direct "Alzheimer label" because astrocyte activation can arise from multiple injury pathways, not exclusively from Alzheimer’s disease. This distinction is crucial for guiding subsequent clinical investigation and interpretation of results.
Identifying Higher-Risk Subgroups: Thresholds and Effect Sizes
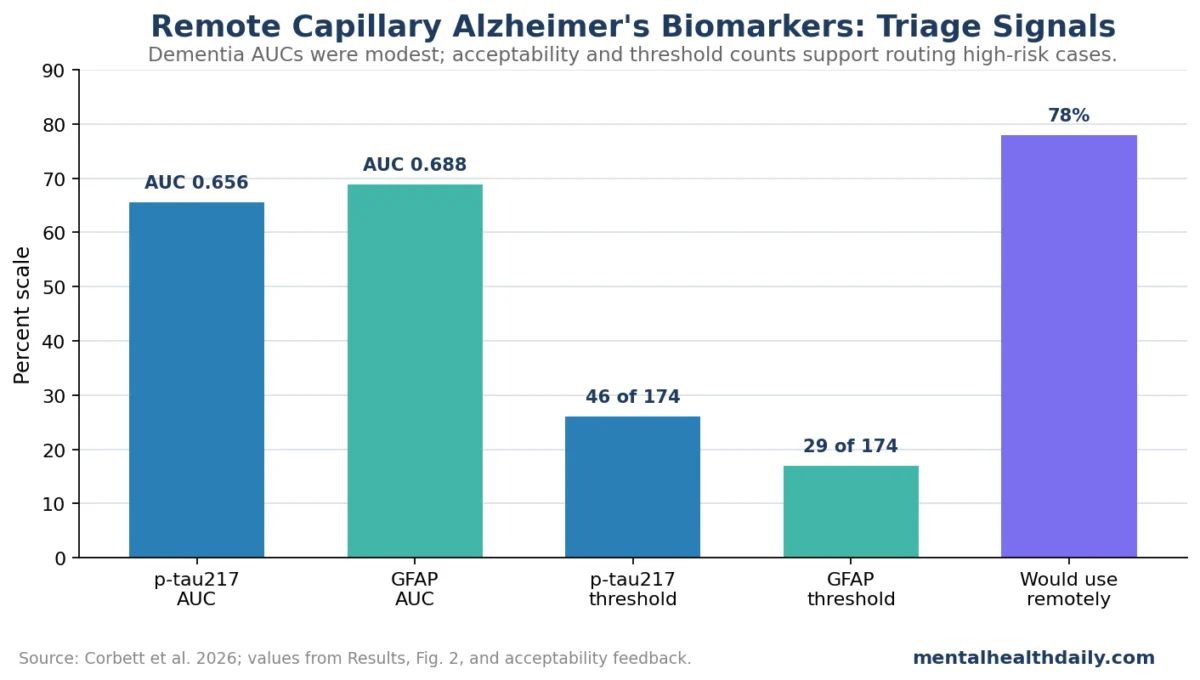
To further refine the utility of these remote tests, Corbett et al. established prespecified 85% specificity thresholds: 0.016 pg/ml for capillary p-tau217 and 12.45 pg/ml for capillary GFAP. These thresholds are designed to identify individuals who are most likely to have underlying pathology, while minimizing false positives. Applying these thresholds, the study identified 46 participants (26% of the cohort) with elevated p-tau217 and 29 participants (17%) with elevated GFAP.
Crucially, individuals exceeding these thresholds performed demonstrably worse on several cognitive and functional measures. For p-tau217, the memory difference between those above and below the threshold was quantified with a Cohen’s d of 0.548 (p = 0.020), indicating a medium effect size. Similarly, IADL difference had a Cohen’s d of 0.542 (p = 0.017), and IQCODE difference was even larger at d = 0.657 (p = 0.001), representing a large effect size. For GFAP, the IADL difference was more pronounced at d = 0.754 (p = 0.004), a large effect, while executive function showed a medium effect at d = 0.541 (p = 0.016). Cohen’s d values provide a standardized measure of the difference between two groups, indicating the practical significance of the findings beyond statistical significance.

A vital aspect of validating a remote collection method is ensuring its results align with established laboratory measures. The PROTECT study confirmed this alignment: the same thresholds were recognizable in venous plasma. Plasma p-tau217 effectively discriminated the capillary p-tau217 threshold group with an Area Under the Curve (AUC) of 0.785, and plasma GFAP discriminated the capillary GFAP threshold group with an impressive AUC of 0.895. These high AUC values indicate excellent agreement between the remote fingerprick samples and traditional venous blood draws, confirming that the remote kit produces clinically useful and reliable biomarker values, rather than isolated artifacts.
Capillary Blood Testing: A Triage Tool, Not a Stand-Alone Diagnosis
Despite the promising correlations and alignment with venous blood, the study firmly positions remote capillary sampling as a triage tool, not a diagnostic one. The paper’s strongest clinical idea centers on a combined triage profile: identifying individuals with elevated p-tau217 above the 85% specificity threshold and memory performance low enough to meet age-associated cognitive decline criteria. This combination is proposed as a pragmatic strategy to identify individuals who should be prioritized for formal dementia evaluation faster than reliance on symptom questionnaires alone.
The AUC values further explain this critical boundary. Capillary p-tau217 achieved an AUC of 0.656, and GFAP an AUC of 0.688, in separating dementia from non-dementia status. While these values are better than chance, they are not considered diagnostic-grade. Diagnostic tools typically require much higher AUCs (e.g., >0.85 or >0.90) to ensure sufficient sensitivity and specificity to confidently diagnose or rule out a condition. An AUC of 0.656 signifies considerable overlap between dementia and non-dementia cases on capillary p-tau217, meaning many individuals without dementia might still show elevated levels, and vice-versa. Furthermore, a normal result from a remote test cannot rule out non-Alzheimer causes of cognitive decline, early pathology below the detection threshold, or future conversion to dementia.
The clinical role of remote p-tau217 and GFAP is therefore defined as sorting risk, reducing screen failures for clinical trials, and directing scarce specialist appointments towards individuals with a higher biological signal. The researchers emphatically state that these tests should not be used to tell a person at home that they have Alzheimer’s disease. The distinction between risk sorting and diagnosis is not merely semantic; it carries profound implications for patient care, psychological well-being, and resource allocation. GFAP, being less disease-specific, further complicates direct diagnostic interpretation, as astrocyte activation can increase due to vascular injury, inflammation, general neurodegeneration, or mixed pathologies.
The most useful application of these tests, therefore, is as a referral aid. The blood result should be combined with a comprehensive clinical picture, including detailed memory performance assessments, reports of daily function, medication reviews, depression screenings, sensory assessments (e.g., hearing and vision), and a thorough vascular-risk history. Only after integrating these multiple data points should a decision be made regarding the need for confirmatory imaging (such as amyloid or tau PET scans), cerebrospinal fluid testing, or specialist neurological evaluation. This holistic approach ensures that individuals receive appropriate, personalized care and avoids premature or inaccurate labeling.
Ensuring a Confirmatory Pathway and Addressing Access Barriers
The utility of capillary biomarkers is contingent upon the existence of a well-defined subsequent step. A positive remote result should never leave a patient with a vague label and no clear path forward. Instead, it must trigger a structured sequence of cognitive testing, medical review, and, when appropriate, confirmatory assessment. The study outlines three essential jobs within a workable pathway: initial biomarker testing (the remote fingerprick), comprehensive clinical assessment (integration of cognitive, functional, and medical history), and confirmatory workup (specialized imaging or CSF analysis).
Remote testing has a significant "access effect," fundamentally changing who can be reached by early detection efforts. Many individuals with early cognitive impairment never enter specialist pathways due to barriers such as travel distance, lack of rural access to clinics, limited clinic capacity, or the burden of trial screening protocols. A mailed capillary kit can effectively lower these barriers, bringing initial screening directly to the patient’s home. However, lowering the barrier to access simultaneously increases the responsibility to avoid overdiagnosis and ensure that follow-up care is equitable and comprehensive.
A critical "boundary condition" highlighted by the study is the need to differentiate between p-tau217 and GFAP. P-tau217 is more closely linked to Alzheimer’s biology, while GFAP may identify broader neuroinflammatory or vascular risk. A triage algorithm that treats both markers as interchangeable "Alzheimer positive" signals would flatten the most useful distinction provided by this research, potentially leading to misdirected follow-up.
Immediate Benefits for Clinical Trials, Future for Routine Screening
Clinical trials represent perhaps the most immediate and impactful early use case for remote fingerprick testing. Alzheimer’s prevention and early-intervention trials often require screening large cohorts of individuals to identify a smaller, eligible group with a specific biomarker profile (e.g., amyloid positivity). Fingerprick p-tau217 could significantly reduce expensive screen failures by pre-identifying people who are more likely to have confirmatory amyloid or tau evidence, thereby streamlining recruitment and reducing the overall cost and logistical burden of trials.
Routine population screening, however, presents a harder claim. For any screening program to be widely implemented, there must be robust evidence that testing improves patient outcomes, reduces harms (e.g., anxiety from false positives, unnecessary procedures), and does not create avoidable distress. A cross-sectional correlation study, while informative, cannot fully answer these complex implementation questions. Longitudinal follow-up is the "missing link" here. The most valuable future outcome is not merely whether a capillary marker correlates with memory on a single date, but whether that marker accurately predicts conversion to dementia, faster cognitive decline, or eligibility for treatment trials over several years. This is the crucial evidence required before remote screening can transition from triage research into routine primary-care pathways.
The "practical threshold" for the evidence is strong enough to justify more validation of remote triage, particularly in trial recruitment and enriching specialist referrals. It is not, however, strong enough to market home fingerprick testing as a direct-to-consumer Alzheimer’s diagnosis. The equity argument is strongest when the test expands access to follow-up care rather than replacing it. A mailed kit can indeed reach individuals living far from memory clinics, but the result still necessitates interpretation by a skilled clinician who can consider a multitude of factors, including medications, alcohol use, sleep patterns, depression, sensory impairment, vascular risk, educational background, and day-to-day functional status.
"False-positive management" is another key consideration. A person with elevated GFAP and known vascular disease may primarily require aggressive vascular-risk management, rather than an Alzheimer’s label. Conversely, a person with elevated p-tau217 and declining memory may indeed need a confirmatory Alzheimer’s workup. Keeping these routes separate and tailored to the individual’s full clinical profile is what makes the biomarker pair clinically useful. Furthermore, implementation also requires a plan for managing "low-signal results." A low capillary biomarker result should never dismiss a caregiver’s report of worsening memory, medication errors, falls, hallucinations, or financial mistakes. Instead, it should narrow the immediate Alzheimer-biomarker probability while keeping the broader differential diagnosis open. This is especially important in primary care, where conditions like depression, sleep apnea, anticholinergic medications, alcohol exposure, hearing loss, and cerebrovascular disease can all mimic early dementia symptoms for families and general practitioners.
In conclusion, the 2026 PROTECT study offers a transformative vision for early Alzheimer’s risk assessment, leveraging the power of accessible, self-administered fingerprick blood tests. While the research unequivocally supports the role of these biomarkers in remote triage and enhancing the efficiency of clinical trials, it critically underscores the need for a comprehensive clinical context and a well-defined confirmatory pathway. The future of Alzheimer’s care hinges on continued validation through longitudinal studies, ensuring that innovations in remote screening truly expand equitable access to timely, accurate, and holistic care, without overstepping the boundaries of diagnostic certainty.

