

The fitness and strength and conditioning industry is currently navigating a significant paradigm shift regarding the language and methodologies used during initial client assessments. For decades, the professional standard involved a "deficit-based" model, where practitioners focused on identifying physical "dysfunctions" to justify corrective interventions. However, emerging evidence and a maturing professional landscape are leading many experts to reconsider the use of pathologizing language. The term "dysfunction," once a hallmark of the sophisticated trainer, is increasingly viewed as a potential barrier to client progress, psychological well-being, and long-term retention.
This transition reflects a broader movement within the health and wellness sector to move away from the "medicalization" of human movement. When a fitness professional highlights a laundry list of perceived flaws—such as anterior pelvic tilt, internally rotated shoulders, or minor asymmetries—during a first meeting, the result is often the induction of the "nocebo effect." This phenomenon occurs when negative expectations or labels lead to a decrease in physical performance or an increase in perceived pain, even in the absence of a physiological injury.
The Rise and Critique of the Corrective Exercise Era
To understand the current state of movement assessment, one must look at the chronology of the fitness industry over the last thirty years. In the 1990s and early 2000s, the industry moved away from a pure bodybuilding and aesthetics focus toward "functional training." This era saw the rise of formalized assessment systems, such as the Functional Movement Screen (FMS) and various "Corrective Exercise" certifications.
These systems were designed to bridge the gap between physical therapy and personal training. They provided trainers with a structured way to "audit" movement, seeking to identify "dysfunctions" that might lead to future injury. While well-intentioned, this era created a culture where trainers often felt the need to prove their value by finding "problems" to "fix." By 2010, it was common practice for a new gym member to be told they were "broken" or "dysfunctional" before they were ever allowed to lift a significant weight.
Critics of this era argue that the industry overcorrected. By focusing so heavily on minor deviations from a "perfect" postural ideal, trainers inadvertently fostered kinesiophobia—an irrational fear of movement—in their clients. This historical context explains why modern industry leaders are now advocating for a more "movement-optimist" approach, where the focus is on what the client can do rather than what they cannot.
Clinical Pathology versus Functional Variation: The Scapular Case Study
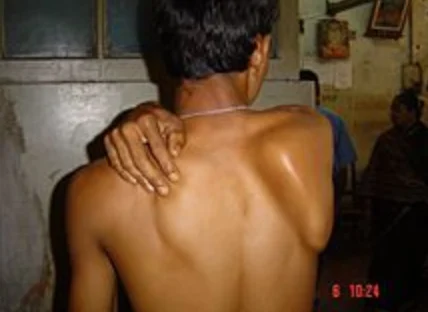
A primary example of the misuse of clinical terminology is the diagnosis of "scapular winging." In a clinical or neurological setting, true scapular winging is a serious medical condition. It typically involves a palsy of the long thoracic nerve, which prevents the serratus anterior muscle from pinning the shoulder blade against the rib cage. This is a legitimate "dysfunction" that requires specialized medical intervention, often involving neurological testing and manual therapy.
However, in the context of a commercial gym, the term is frequently used to describe any shoulder blade that appears prominent or moves with minor asymmetry. Data suggests that a significant percentage of the asymptomatic population exhibits some degree of scapular prominence or dyskinesis. When a trainer labels this as a "dysfunction" to a layperson, they are often conflating a common movement variation with a rare neurological pathology.
Recent studies in the field of sports medicine indicate that many "abnormalities" found in assessments are not predictive of pain or injury. For instance, research in the British Journal of Sports Medicine has shown that structural "flaws" like disc bulges or labral tears are frequently found in high-performing, pain-free athletes. By extension, a "winging" scapula in a client who feels no pain and possesses functional range of motion may not be a dysfunction at all, but rather a unique adaptation to their lifestyle or anatomy.
The Psychological Impact of Pathologizing Language
The shift in professional tone is backed by psychological research into the "Biopsychosocial Model" of health. This model posits that a person’s physical state is inextricably linked to their psychological state and social environment. When a trainer uses words like "dysfunction," "imbalance," or "broken," they are influencing the "bio" through the "psycho."
If a client believes their spine is "unstable" due to a trainer’s assessment, they are likely to move with excessive stiffness and guarding. This guarding can, ironically, lead to the very back pain the trainer was trying to prevent. The industry is now seeing a reaction from related parties, including physical therapists and sports psychologists, who urge trainers to use "green light" language. Instead of telling a client their back is weak, a trainer might say, "We are going to focus on strengthening your posterior chain to support your goals."
This change in communication strategy is not merely about being "polite"; it is an evidence-based approach to improving outcomes. When clients feel capable and resilient, they are more likely to adhere to their programs and experience better physiological adaptations to stress.
The Role of Load in "Fixing" Movement
One of the most significant arguments against the "dysfunction" narrative is the efficacy of traditional strength training in resolving movement issues. For years, the standard protocol for a "dysfunctional" movement was "corrective exercise purgatory"—a regimen of low-intensity, isolated movements like foam rolling, bird-dogs, and light band work.
While these exercises have their place in a warm-up, data indicates that "loading" a movement is often the most efficient way to improve it. In the case of minor scapular prominence, engaging in compound movements like rows, presses, and loaded carries often provides the necessary stimulus for the nervous system to better organize the shoulder complex.
Training under load forces the body to find the most efficient path of force transmission. In many cases, what looks like a "dysfunction" in an unweighted assessment disappears once the client is asked to move a meaningful weight. This suggests that many perceived issues are not structural failures but rather a lack of "movement literacy" or motor control that can be resolved through standard progressive overload rather than specialized corrective protocols.
Economic and Business Implications for Fitness Professionals
Beyond the clinical and psychological aspects, there is a clear business case for reducing the use of the word "dysfunction." The fitness industry is a service-based economy where client retention is the primary driver of profitability. The "Customer Acquisition Cost" (CAC) in the fitness industry is high, meaning trainers must maximize the "Lifetime Value" (LTV) of each client.
An initial assessment that makes a client feel physically inferior or "broken" creates a negative emotional association with the gym. If a client leaves their first session feeling like a "walking ball of fail," the likelihood of them purchasing a long-term training package decreases significantly. Industry analysis suggests that trainers who adopt a "strength-first" or "capability-based" assessment model see higher conversion rates. By highlighting what a client does well and framing "corrections" as "performance enhancements," trainers build a relationship based on empowerment rather than fear.
Broader Impact and Future Directions
The move away from "dysfunction" represents the professional maturation of the fitness industry. It marks a transition from a "guru-centric" model—where the trainer possesses secret knowledge of the client’s flaws—to a "client-centered" model.
In the coming years, it is expected that certification bodies will continue to update their curricula to emphasize movement optimism and the biopsychosocial model. The integration of wearable technology and AI-driven movement analysis may also provide more objective data, potentially reducing the subjective "pathologizing" that occurs during human-led assessments.
Ultimately, the goal of any fitness professional is to facilitate health and performance. By retiring the word "dysfunction" and focusing on the vast potential for adaptation in the human body, trainers can better serve their clients, foster a more positive gym culture, and align themselves with the latest findings in sports science and psychology. The industry’s evolution toward more constructive language is not just a change in vocabulary; it is a fundamental shift in how we perceive human resilience.

