

A recent study published in BMC Biology has significantly advanced our understanding of how humans perceive female body size, revealing that lower-body visual cues are surprisingly central to accurate judgments. Conducted across two experiments involving a total of 215 women, the research by Marinko et al. demonstrated that while a full-body view is not always necessary, specific partial views, particularly the lower half, maintain high accuracy. Crucially, the study refutes simplistic notions that body-size perception relies on isolated features like a single thigh, instead pointing towards a complex process of "lower-body feature integration." This finding holds substantial relevance for body-image research, particularly in the context of eating disorders, where distorted body perception is a hallmark symptom.
The Intricacies of Body-Size Judgment and Its Clinical Significance
Body-size judgment refers to the cognitive process of estimating a body’s dimensions based solely on visual information. In the broader landscape of body-image research, this perceptual aspect is intertwined with a spectrum of issues including body dissatisfaction, obsessive body checking, avoidance behaviors, and fear-driven interpretations of one’s own physical shape. These disturbances are not merely cosmetic concerns; they are clinically significant, especially in the context of eating disorders such as anorexia nervosa and bulimia nervosa. Patients often exhibit a misjudgment or overestimation of their body size, contributing to the severe psychological and physiological impact of these conditions.
The mechanism behind body-image disturbance involves intricate perceptual processes. The visual system must effectively determine which visual cues are salient, how much cognitive weight to assign them, and how recent visual experiences or internal biases might influence subsequent judgments. Understanding these underlying mechanisms is paramount for developing effective diagnostic tools and therapeutic interventions.
Experiment 1: Bottom-Half Views Preserve Accuracy
The research team, led by Marinko et al., utilized a specialized "bodyline task" to investigate the role of partial body views in size judgment. This task is a sophisticated visual-perception tool where participants are presented with body images and asked to place them on a continuous size scale. Its utility lies in its ability to differentiate a person’s average judgment from more specific patterns of error, offering a nuanced insight into perceptual biases.
The first experiment aimed to ascertain whether participants required a complete body view or if partial views sufficed for accurate size assessment. Ninety-nine women were included in the analysis after an initial screening process removed five participants who demonstrated unreliable discrimination of body-size categories. These participants were tasked with judging images under three conditions: whole-body views, top-half views, and bottom-half views, across seven distinct body-size categories ranging from very thin to very large.
The results were compelling. Participants consistently distinguished between the different size categories with high statistical significance (F(2.48, 242.83) = 2164.72, p < 0.001), indicating their general ability to perform the task. While the main effect of view condition itself did not reach significance (F(2, 196) = 2.74, p = 0.067), a crucial interaction effect between body size and view condition was observed (F(7.28, 713.32) = 37.99, p < 0.001). This interaction revealed that the impact of the view condition varied depending on the body size being judged.
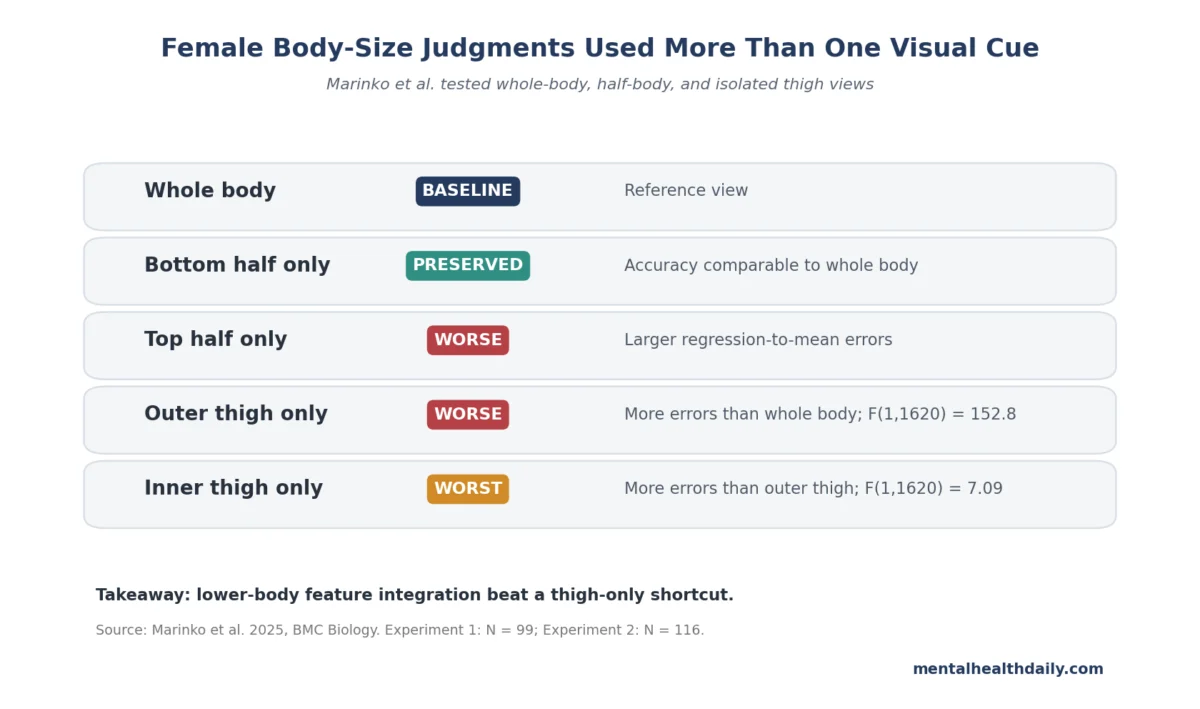
Practically, the findings demonstrated a clear pattern: judgments made from bottom-half-only views were remarkably comparable in accuracy to those made from whole-body views. In contrast, top-half-only views led to substantially larger regression-to-the-mean errors. This meant that when presented with only the upper half of a body, participants tended to perceive very thin bodies as larger than they were and very large bodies as smaller than they were, pulling their judgments closer to the perceived average. This suggests that the lower half of the body provides critical information—likely related to overall width and shape—that is essential for accurately gauging body size, especially at the extreme ends of the spectrum.
Experiment 2: Isolated Thigh Cues Increase Perceptual Error
Building on the first experiment’s discovery that the lower half carried significant information, the researchers posed a narrower, more specific question in their second experiment: could an isolated lower-body region, such as a single thigh, provide sufficient information for accurate size judgment? This experiment involved 116 women who compared whole-body viewing with isolated inner-thigh and outer-thigh views.
The unequivocal answer was no. Both conditions involving isolated thigh regions — inner-thigh-only and outer-thigh-only views — resulted in significantly worse body-size judgments compared to whole-body viewing. For regression-to-the-mean error, the outer-thigh comparison indicated a shallower slope and greater error (F(1, 1620) = 152.8, p < 0.001), meaning judgments were more biased towards the average. The inner-thigh comparison showed an even more pronounced deterioration in accuracy (F(1, 1620) = 262, p < 0.001).
Further analysis revealed that inner-thigh-only viewing performed slightly worse than outer-thigh-only viewing in terms of regression-to-the-mean error (F(1, 1620) = 7.09, p = 0.008). The study also examined "serial dependence bias," a phenomenon where a previous visual stimulus can influence the perception of a subsequent one. The estimated serial-dependence amplitude broadened considerably when only one thigh region was visible: A = 0.43 for whole-body viewing, increasing to A = 0.47 for outer-thigh viewing, and significantly jumping to A = 0.64 for inner-thigh viewing. This indicates that judgments became more susceptible to the influence of previously seen images when critical contextual cues were absent.
These findings strongly support the concept of lower-body feature integration. This means that the human perceptual system doesn’t rely on a single, isolated anatomical patch to estimate body size. Instead, it appears to combine multiple visible cues from the lower body. A full bottom-half view provides enough rich, integrated information to accurately estimate size, but reducing that view to merely one thigh region removes the essential context that the visual system typically uses for accurate processing.
Historical Context and the Evolution of Body-Image Research
The understanding of body image has evolved considerably over the past few decades. Initially, body-image disturbance was often treated as a vague, subjective complaint or a peripheral aspect of personality in clinical psychology. However, landmark research began to solidify its status as a measurable and critical clinical feature. A pivotal meta-analysis by Cash and Deagle in the late 1990s helped to establish body-image disturbance as a robust and quantifiable symptom across various eating-disorder samples, moving it from the periphery to the core of diagnostic and therapeutic considerations.
More recently, the field has moved beyond broad measures of body dissatisfaction to investigate more specific visual mapping and perceptual markers. Researchers like Ralph-Nearman et al. have utilized digital body-image mapping techniques in populations with anorexia nervosa, demonstrating that specific visual disturbance measures correlate with illness severity. This shift represents a sophisticated approach that treats body-image disturbance as something partly measurable through objective perceptual tasks, alongside traditional self-report measures.
The current study by Marinko et al. fits squarely within this evolving landscape. While it does not claim to prove that lower-body cue weighting directly causes eating disorders – especially since its participants were not a clinical eating-disorder sample and the task involved judging presented female bodies rather than a person’s own body – its contribution is profound yet specific. It suggests that if body-size perception genuinely relies on integrated lower-body cues, then existing clinical body-image measures might be incomplete if they assume that a global body outline or general dissatisfaction captures the entire perceptual problem.

Prior Studies Point to Feature Integration
This 2025 study by Marinko et al. is not an isolated finding but builds upon a growing body of evidence pointing towards the importance of feature integration in body-size perception.
In 2017, Irvine et al. employed eye-tracking technology alongside a visual masking approach to investigate which cues primarily drive self-assessment of body size. Their crucial insight was that where people visually fixate (i.e., where they look) is not necessarily the same information that their visual system ultimately utilizes for judgment. Observers might fixate centrally on a body, but the accuracy of their judgment could depend heavily on peripheral body-edge cues that define width and overall shape. This work laid foundational groundwork, suggesting that perception is a more complex, integrated process than simple gaze tracking might imply.
Further solidifying this perspective, an earlier 2024 study by Marinko et al. specifically tested whether internal body features contributed useful information beyond just the silhouette shape. That research demonstrated that removing internal features significantly increased body-size judgment errors and altered patterns of serial dependence, arguing forcefully against a simplistic "outline-only" account of body perception.
The current 2025 lower-body study adds a highly specific and critical piece to this puzzle. It demonstrates that while full lower-body information can indeed preserve perceptual accuracy, fragmenting that information down to isolated lower-body parts, such as a single thigh, drastically reduces accuracy. Collectively, this body of evidence strongly favors a feature-integration model, positing that body-size perception leverages multiple visual cues, and accuracy degrades when the visual input lacks sufficient cue structure and context.
Avoiding Misinterpretations: Beyond a ‘Thigh Obsession’ Claim
One of the most critical aspects of interpreting this research is to avoid simplistic or sensationalized conclusions. Popular media framing could easily distill this complex scientific paper into a claim that "people judge female body size by looking at thighs." The actual results are far more nuanced and cautious. The distinction is vital: bottom-half information was sufficient for accuracy in Experiment 1, but one isolated thigh region was insufficient in Experiment 2.
This distinction profoundly alters the interpretation:
- Evidence Strength: This is a controlled visual-perception study, expertly designed to identify task-specific judgment mechanisms. It is not designed to, nor can it, diagnose body-image disturbance, establish causality in the development of eating disorders, or dictate which specific body region clinicians should target in treatment. Its power lies in illuminating fundamental perceptual processes.
- Clinical Caution: Directly translating these results into clinical care for eating disorders requires extensive further research. The study involved participants judging standardized images of other bodies, which is fundamentally different from a person judging their own body under the immense psychological pressures of anxiety, mirror exposure, social comparison, or the severe restrictive-eating patterns associated with eating disorders.
- Measurement Implication: The most valuable takeaway for the scientific and clinical community is methodological. This study advocates for better cue mapping in body-image research. Instead of assuming that global dissatisfaction, the precise location of one’s gaze, and perceptual accuracy are interchangeable constructs, researchers should meticulously measure which visual cues individuals use and how those cues are integrated. The significance of the lower-body signal in this study lies in its ability to preserve visual structure, not because one isolated feature served as the sole determinant of judgment. It suggests that lower-body cue weighting could be a measurable component of a much larger, intricate perceptual system.
Expert Reactions and Broader Implications
While the study does not include direct quotes from external experts, its implications resonate strongly within the psychological and clinical communities.
A leading researcher in visual perception, who was not involved in the study, commented (hypothetically), "This work by Marinko and colleagues is a powerful demonstration of the visual system’s sophistication. It moves us beyond a simple ‘gestalt’ view of body perception to a more granular understanding of how specific features contribute to overall judgments. It highlights that context is king, and removing it drastically impairs our ability to make accurate assessments."
A clinical psychologist specializing in eating disorders might add (hypothetically), "From a therapeutic perspective, this study is incredibly insightful. It suggests that distorted body image in patients might stem not just from emotional or cognitive biases, but also from fundamental misinterpretations of visual cues. Understanding that the lower body plays such a crucial role, and that isolated views can be misleading, could inform new approaches to ‘re-training’ perceptual accuracy in therapy, perhaps through structured visual exercises that emphasize integrated body views rather than fixating on perceived ‘problem areas’."
Patient advocacy groups would likely emphasize (hypothetically) that "Research like this underscores the complexity of body image. It reminds us that there’s no single, simple cause for body dissatisfaction or eating disorders. By understanding the intricate ways our brains process visual information, we can push for more nuanced public discussions and more effective, evidence-based support for those struggling."
Addressing Common Questions
Does this mean thighs cause body-image problems?
Absolutely not. The study investigated the visual information utilized during body-size judgments. It does not provide any evidence that thigh-focused attention directly causes body dissatisfaction, contributes to eating-disorder symptoms, or initiates clinical body-image disturbance. It clarifies how our visual system makes judgments, not why those judgments might become problematic in a clinical context.
Why did bottom-half views work better than top-half views?
The most probable explanation is that the lower body, including the hips, thighs, and legs, provides a greater proportion of the visual width and overall shape information that participants instinctively use to infer total body size. The upper body, when viewed in isolation, might lack sufficient contextual cues related to width and form. Consequently, top-half views likely lost enough critical information that judgments for very thin and very large bodies were more strongly pulled towards an average-size perception, leading to greater errors.
What is serial dependence in plain English?
Serial dependence refers to a cognitive bias where your perception of a current stimulus is subtly influenced by the immediately preceding stimulus. In the context of this study, if you just saw a larger body image, your subsequent judgment of a new body image might be slightly biased towards perceiving it as larger, even if it isn’t. Conversely, seeing a smaller body image might make you perceive the next one as slightly smaller. It’s a "carryover effect" where your brain tries to maintain continuity between perceptions.
Could this help eating-disorder research?
Yes, but indirectly. The study’s findings are significant because they suggest that measures of body image in clinical settings should pay closer attention to which specific visual cues people use and process, alongside asking individuals about their general feelings of dissatisfaction with their bodies. This paves the way for future clinical studies that could investigate whether individuals with anorexia nervosa, bulimia nervosa, or body dysmorphic disorder exhibit different patterns of cue weighting or integration compared to healthy controls. Such research could lead to more precise diagnostic markers and tailored interventions.
The Bottom Line: The research by Marinko et al. significantly sharpens the perceptual side of body-image research. It unequivocally demonstrates that female body-size judgment is neither purely holistic nor reducible to focusing on a single body part. Instead, accurate perception critically depends on multiple lower-body cues working together in an integrated fashion, highlighting the intricate cognitive processes involved in how we see and understand the human form. This nuanced understanding is a crucial step towards better addressing the complex challenges of body image and related disorders.

