

The fitness and strength conditioning industry is currently undergoing a significant paradigm shift regarding how professionals assess, communicate, and "correct" human movement. For over two decades, a dominant trend in personal training and physical therapy has focused heavily on identifying "dysfunctions"—a term used to describe perceived deviations from an idealized anatomical norm. However, emerging evidence and a growing consensus among industry veterans suggest that the over-labeling of movement patterns as "dysfunctional" may be counterproductive, potentially causing psychological harm to clients while failing to produce superior physical outcomes.
The core of this debate centers on the initial assessment process, where fitness professionals often provide a "laundry list" of anatomical flaws to prospective clients. Common labels include internally rotated shoulders, anterior pelvic tilt, upper back kyphosis, and lack of thoracic rotation. While these observations may be anatomically accurate in a vacuum, the practice of framing them as "broken" components that require "fixing" is increasingly viewed as a flawed business and clinical strategy. Experts argue that this approach often leads to "corrective exercise purgatory," where clients spend months performing low-intensity mobility drills rather than engaging in the high-intensity training required to build genuine resilience and strength.
The Anatomy of a Misdiagnosis: The Case of Scapular Winging
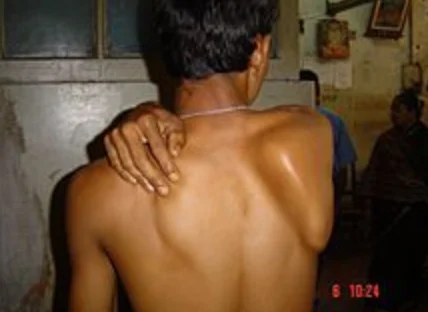
To understand the stakes of this shift, one must examine specific examples of movement patterns that are frequently mislabeled. Scapular winging—a condition where the medial border of the shoulder blade protrudes from the rib cage—serves as a primary case study. In a clinical, medical context, true scapular winging is a serious neurological diagnosis. It typically results from a palsy or injury to the long thoracic nerve, which innervates the serratus anterior muscle. When this nerve fails to function, the shoulder blade loses its structural congruency with the rib cage, leading to significant functional impairment that often requires specialized manual therapy or neurological intervention.
However, in the context of a standard gym floor, many trainers identify "winging" in clients who do not possess a neurological deficit. Instead, these clients may simply exhibit movement variability or a temporary lack of muscular control under specific conditions. Industry analysts note that "corrective" protocols, such as prone trap raises or forearm wall slides, are frequently prescribed for these individuals. While these exercises are not inherently harmful, they often distract from more effective interventions. Data suggests that for the vast majority of the population, "fixing" these movement patterns is achieved more efficiently through the application of load and progressive resistance training rather than isolated corrective drills. Load serves as a functional "nudge," forcing the body to find more stable and efficient positions to manage the weight.
A Chronology of Movement Philosophy in the Fitness Industry
The evolution of the "dysfunction" narrative can be traced through several distinct eras of fitness philosophy over the last forty years.
- The Aesthetic Era (1980s – 1990s): During this period, fitness was largely dominated by bodybuilding culture. Assessments were primarily visual and focused on muscle size and body fat percentage. Movement quality was rarely a primary concern, provided the individual could perform the lifts necessary for hypertrophy.
- The Functional Training Boom (Late 1990s – Early 2000s): Led by pioneers in physical therapy and strength coaching, the industry shifted toward "functional" movement. This era introduced the idea that the body works as a kinetic chain. While beneficial, it laid the groundwork for hyper-analyzing every joint’s contribution to a movement.
- The Corrective Exercise Era (2005 – 2015): This decade saw the rise of formalized movement screens, such as the Functional Movement Screen (FMS). During this time, the term "dysfunction" became a staple of the trainer’s vocabulary. The industry began to pathologize normal human variation, leading to a surge in "pre-hab" and corrective protocols that often preceded any actual strength training.
- The Resilience and Evidence-Based Era (2016 – Present): The current era is characterized by a "re-maturation" of the industry. Professionals are increasingly recognizing that the human body is robust and adaptable, not a fragile machine that "breaks" because of a slight pelvic tilt. There is a renewed focus on the psychological impact of coaching language and the efficacy of general strength training over hyper-specific corrections.
Supporting Data and the Impact of the Nocebo Effect
The psychological implications of being told one is "dysfunctional" are supported by a growing body of research into the "nocebo effect." While a placebo is a harmless substance that creates a positive effect through belief, a nocebo is a harmless statement or treatment that creates a negative effect through the expectation of harm.
Studies in the journal Pain and The Spine Journal have indicated that a patient’s belief about their structural integrity is a significant predictor of chronic pain. When a fitness professional tells a client they have a "herniated disc" or a "dysfunctional shoulder," they may inadvertently increase the client’s sensitivity to pain and decrease their willingness to move. This creates a cycle of kinesiophobia (fear of movement), which is often more debilitating than the original physical "flaw."
Furthermore, data comparing the effectiveness of "corrective" exercises versus general resistance training often shows no significant difference in long-term pain reduction or performance improvement for non-clinical populations. A 2014 meta-analysis regarding the Functional Movement Screen found that while it could identify movement patterns, its ability to predict injury risk or dictate necessary corrections was limited. This has led many high-level strength coaches to adopt an "audit" approach rather than a "diagnostic" approach—observing how a client moves to determine a safe starting point, rather than to list their failures.
Perspectives from the Field: The Shift in Professional Standards
Leading strength coaches and physical therapists are increasingly advocating for a "strength-first" model. The consensus is that the role of the fitness professional is to ascertain what will set a client up for success based on their goals, injury history, and current ability level, rather than to act as a pseudo-medical diagnostician.
"It is our job to audit movement," says one industry expert, "but one of the worst things you can do is highlight dysfunction and make people feel broken out of the gate." This sentiment reflects a broader trend toward "empowerment coaching." Instead of telling a client they cannot squat because of "ankle dysfunction," a modern coach might simply adjust the client’s stance or use a different squat variation that allows them to train effectively immediately.
This shift also has significant implications for business and client retention. The "dysfunction" model often leads to a high "churn" rate, as clients become discouraged by a lack of progress in "corrective" drills or feel intimidated by the suggestion that they are anatomically compromised. Conversely, programs that focus on what the client can do tend to see higher engagement and better physical adaptations.
Broader Implications for the Future of Fitness and Healthcare
The move away from the "dysfunction" narrative has the potential to reshape the relationship between the fitness industry and the healthcare system. As personal trainers move away from making medicalized "diagnoses," the boundary between fitness coaching and clinical physical therapy becomes clearer and more professional. This allows for better referrals and a more collaborative approach to human health.
Moreover, this shift addresses a growing public health concern: sedentary behavior. If the barrier to entry for exercise is a perceived need to "fix" a dozen "dysfunctions" first, fewer people will engage in the life-prolonging benefits of resistance training. By simplifying the assessment process and prioritizing load and movement over perfection, the industry can reach a broader demographic.
In conclusion, the "dysfunction" era of fitness appears to be waning, replaced by a more nuanced understanding of human movement variability. The focus is shifting from "fixing" a broken machine to "building" a more resilient organism. For the modern fitness professional, the goal is no longer to demonstrate how much a client is a "walking ball of fail" on day one, but to identify the most efficient path toward strength, health, and confidence. As the industry continues to mature, the word "dysfunction" may eventually be relegated to the clinical settings where it belongs, leaving the gym floor as a place for progress rather than pathology.

